Bivalvular Endocarditis with Clinical Manifestations Confounding Peripheral Arterial Occlusive Disease
Article Sidebar
Main Article Content
Abstract
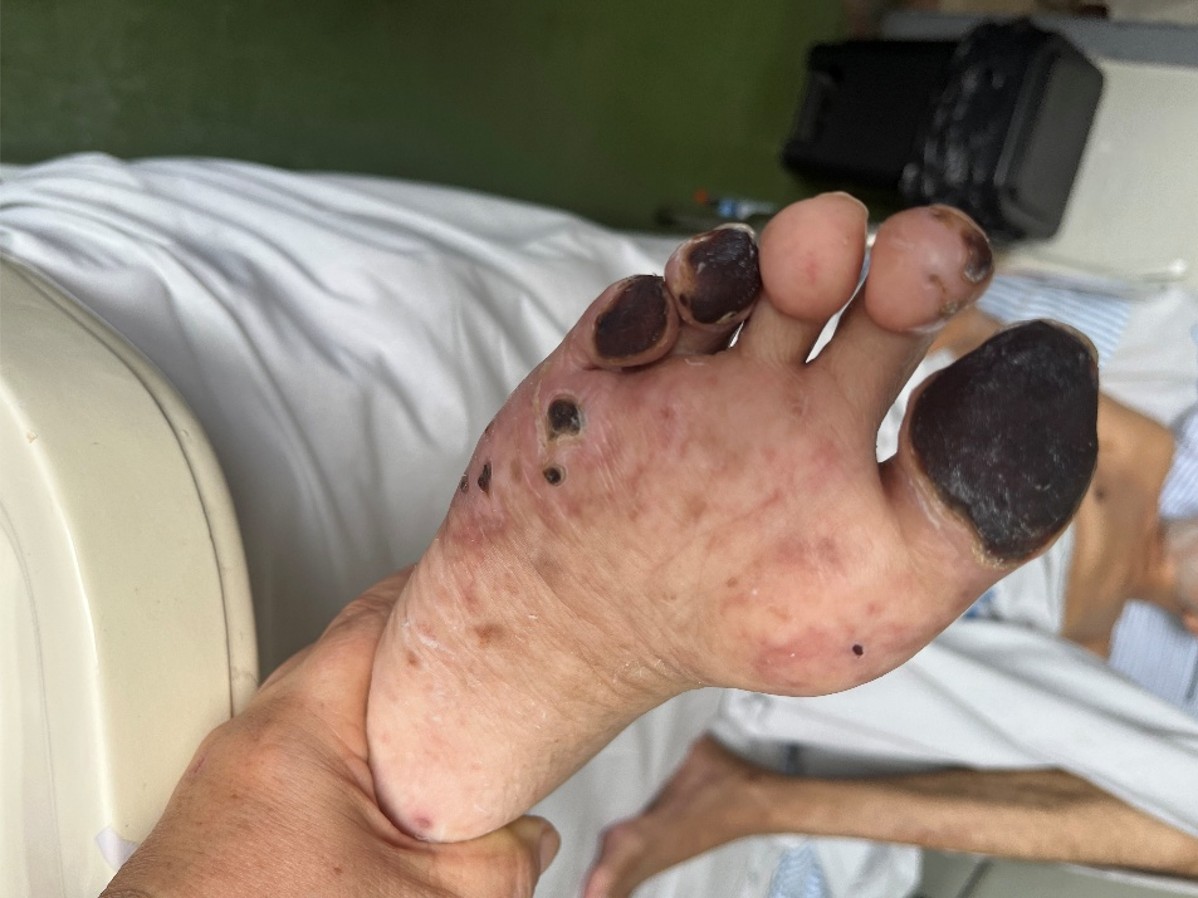
Infective endocarditis (IE) is a serious disease associated with high morbidity and mortality, characterized by infection of the cardiac endothelium, particularly involving native or prosthetic heart valves. In recent decades, an increase in its incidence and a change in its epidemiological profile have been observed, attributed to population aging and the increasing number of invasive interventions. This study aims to report a case of bivalvular infective endocarditis complicated by a peripheral mycotic aneurysm, in which diagnosis was delayed due to the initial interpretation of the vascular manifestation as isolated peripheral arterial disease. This is a 71-year-old patient with cardiovascular comorbidities who presented with prolonged intermittent fever, progressive dyspnea, and an aneurysmal lesion of the right popliteal artery. Diagnostic investigation revealed large vegetations on the mitral and aortic valves on transesophageal echocardiography, associated with severe valvular regurgitation, in addition to positive blood cultures for Streptococcus gallolyticus. The peripheral aneurysm was interpreted as a mycotic aneurysm secondary to a septic embolic event. The patient underwent targeted antibiotic therapy and surgical treatment with mitral and aortic valve replacement associated with myocardial revascularization; however, he developed refractory cardiogenic shock and died in the postoperative period. This case illustrates the diagnostic complexity of subacute infective endocarditis and highlights the importance of early clinical suspicion in the presence of fever of undetermined origin associated with peripheral embolic manifestations, aiming to reduce diagnostic delays, severe complications, and mortality.
Article Details

This work is licensed under a Creative Commons Attribution 4.0 International License.
Authors retain the copyright of their articles and grant the journal the right of first publication under the Creative Commons Attribution (CC BY) license, which allows others to share and adapt the work with proper attribution.
References
Baddour LM, et al. Infective endocarditis in adults: diagnosis, antimicrobial therapy, and management of complications: a scientific statement for healthcare professionals from the American Heart Association. Circulation. 2015;132(15):1435-1486. doi:10.1161/CIR.0000000000000296.
Chambers HF, Bayer AS. Native-valve infective endocarditis. N Engl J Med. 2020;383(6):567-576. doi:10.1056/NEJMcp2000400.
González I, et al. Symptomatic peripheral mycotic aneurysms due to infective endocarditis: a contemporary profile. Medicine (Baltimore). 2014;93(1):42-52. doi:10.1097/MD.0000000000000014.
Habib G, et al. Clinical presentation, aetiology and outcome of infective endocarditis: results of the ESC-EORP EURO-ENDO (European infective endocarditis) registry: a prospective cohort study. Eur Heart J. 2019;40(39):3222-3232.
Li M, et al. Infective endocarditis. Lancet. 2024;404(10450):377-392. doi:10.1016/S0140-6736(24)01098-5.
Osler W. The Gulstonian lectures, on malignant endocarditis. Br Med J. 1885;1(1262):467-470.
Pericàs JM, et al. The RE-ENDO registry: a prospective, interoperable, standardised clinical registry of infective endocarditis patients. Eur Heart J Qual Care Clin Outcomes. 2022;8(2):159-168.
Wilson WR, et al. Vascular graft infections, mycotic aneurysms, and endovascular infections: a scientific statement from the American Heart Association. Circulation. 2016;134(20):e412-e460. doi:10.1161/CIR.0000000000000457.
Sánchez-Pinto AM, et al. Mycotic aneurysms in infective endocarditis: clinical characteristics and outcomes. Clin Infect Dis. 2024;78(3):642-650. doi:10.1093/cid/ciad629.